Why Your Double Chin Has Not Gone, Even Though You Have Lost Weight
Written by Dr. Ashutosh A Shah, M.B.B.S., M.S., M.Ch., D.N.B., Consultant Plastic, Cosmetic and Reconstructive Surgeon, Elegance Clinic, Surat. Reg. no. [REG NO]. 22+ years in facial contouring and body contouring surgery.
Medically reviewed by Dr. Ashutosh A Shah · Published 26 September 2026 · Last reviewed 26 September 2026
A double chin that does not reduce with weight loss is often not mainly fat. The same profile can be produced by loose skin, by banding of the platysma muscle, or by the position of the jawbone itself. Only the fat component responds to weight loss.
If you have lost weight everywhere else and the profile under your chin looks the same in photographs, the usual conclusion is that you have not lost enough. That is frequently the wrong conclusion.
This page is about working out which tissue is actually responsible, because that is the question that decides whether anything you do next will work. It does not discuss treatments, which are covered separately.
Why does weight loss change some double chins and not others?
Because weight loss removes fat and nothing else. If fat is not the main thing producing the profile, losing more of it changes very little.
The structures under the chin are layered: skin on the outside, a layer of fat beneath it, the platysma muscle beneath that, a further fat layer beneath the muscle, and under everything the jawbone and the hyoid bone that set the framework. A full-looking neck can come from any of those, and from more than one at once.
There is a published way of sorting this out. The Dedo classification, described in the StatPearls chapter on neck rejuvenation, divides the ageing neck into six categories rather than treating it as one problem.
What are the six things that produce this profile?
Six, not one. Only one of them is fat, which is the whole reason dieting produces such inconsistent results on this part of the body.
| Category | What is actually happening | Does weight loss help? |
|---|---|---|
| Normal | No structural problem. The profile is within ordinary variation | Not applicable |
| Skin laxity only | Skin has lost its recoil. The tissue underneath may be unremarkable | No, and it can look worse |
| Neck adiposity | Fat, in the layer above the muscle, beneath it, or both | Yes, if it is the layer above |
| Platysmal banding | The muscle's midline fibres have separated, leaving vertical cords | No |
| Retrognathia | The jaw and chin sit further back, so there is less support in front | No |
| Low lying hyoid | The small bone anchoring the floor of the mouth sits low, flattening the angle | No |
Five of the six rows say no. That is the honest explanation for why a successful weight loss can leave this one area looking untouched.
One further cause sits outside this classification and is worth knowing exists: enlargement of a salivary gland under the jaw. It is uncommon, it is described on our companion page on causes and what each treatment does, and it is not something to self-diagnose.
What do the three home tests tell you?
Three tests, taking about a minute, and each one points at a different category. None of them is a diagnosis, and all of them make your consultation shorter and better.
| Test | How to do it | What the result suggests |
|---|---|---|
| The pinch | Sitting upright, gather the tissue under your chin between finger and thumb, then release | A thick soft roll that springs flat suggests fat with reasonable skin. A thin fold that stays creased suggests skin. Very little to gather points elsewhere |
| The clench | Look in a mirror and pull the corners of your mouth down and back hard, as if wincing | Vertical cords standing out from the neck suggest platysmal banding. This is the test that makes bands visible when they hide at rest |
| The profile | Photograph yourself from the side, head level, teeth together, looking straight ahead | A chin that sits behind the lower lip line, or a shallow angle between chin and neck with little tissue to pinch, points to the skeletal categories |
The clench test works because of how the muscle behaves. StatPearls notes that contracting the platysma "causes elevation of the neck with accentuation of the platysmal bands", which is exactly what you are trying to provoke.
Take the photograph rather than relying on the mirror. Most people have never seen their own profile properly, and the front-on view hides the two categories that matter most here.
When is it genuinely fat, and which layer is it in?
Fat is the answer when there is a thick, soft, easily gathered roll and the skin still springs back. But there are two fat layers under the chin and they do not behave the same way.
The superficial layer sits between the skin and the platysma. That is the one you can pinch, and the one weight loss reaches most readily.
Beneath the muscle is a second layer. StatPearls describes it plainly: "Subplatysmal fat occupies the space between the platysma superficially and the deeper strap muscles." The same chapter notes it should not be approached blindly from outside, because of the vessels, nerves and other structures sitting near it.
That distinction matters to you for one reason. A neck that still looks full after weight loss, with very little to pinch, may have fullness in a layer that the pinch test cannot reach and that nothing you do at home will influence. Which layer yours is in is an examination finding, not a self-assessment.
When is it skin that has lost its recoil?
When what you gather is thin and skin-like rather than bulky, and it stays creased for a moment after you let go. Skin that has lost elasticity does not re-drape over a smaller volume underneath.
This is the category that gets worse with successful weight loss rather than better. Removing volume from under skin that cannot retract leaves the same envelope with less to fill it, and the looseness becomes more visible than it was.
Neck skin is also less forgiving than facial skin to begin with. StatPearls notes that neck skin "is thinner and has fewer dermal appendages, making it less resilient" than the skin of the face.
If your pinch test produces a thin fold, further weight loss is unlikely to be the answer, and it is worth knowing that before you set another target.
Why do platysma bands look worse when you talk?
Because they are a muscle, and muscles are more visible when they contract. Bands that are barely there at rest can stand out sharply during speech, laughing or any strong expression.
The platysma is a broad, thin sheet. The StatPearls chapter on the anatomy of the platysma describes it as running from "the fascia of the upper thorax including the clavicle, acromial region, pectoralis major and deltoid muscles" up to the jaw, with "only a small bony insertion, which is on the anterior third of the mandible". It is anchored much more to skin and soft tissue than to bone, which is why it shows through so readily.
The bands themselves are a separation problem. In younger necks the fibres interdigitate across the midline. StatPearls states that "with age, the medial fibers separate", and the neck rejuvenation chapter describes the muscle producing vertical bands "when the medial borders dehisce away from each other and move laterally".
Timing is reasonably predictable. StatPearls records that platysmal bands typically begin to appear "by the age of 55 years with worsening over time". If vertical cords are your main complaint and you are in that age range, the fat question may be a distraction.
What does jaw position have to do with it?
A great deal, and it is the category most often missed. If the chin sits further back, the soft tissue in front of the neck has less to sit on, and the same amount of fat produces a fuller-looking profile.
This is not a subtle theoretical point. Retrognathia, meaning a jaw set back relative to the rest of the face, is its own category in the Dedo classification, sitting alongside fat and skin rather than beneath them.
Two people can carry identical soft tissue under the chin and look completely different in profile purely because of where the chin sits. One of them will lose weight and see a result. The other will not, and will conclude something is wrong with how they diet.
If your profile photograph shows a chin that sits behind the line of your lower lip, that finding belongs in your consultation before anything else is discussed.
Why does the hyoid bone matter, and can it be changed?
The hyoid is a small U-shaped bone in the front of the neck that anchors the floor of the mouth. Where it sits determines how sharp the angle between the chin and the neck can ever be.
A hyoid sitting low, or further forward, produces a shallow, filled-looking angle regardless of how much fat is present. It is category six of the Dedo classification, and it is the reason two people with the same weight, the same age and the same skin can have completely different necks.
On whether it can be changed, the source is unambiguous, and it is the most important sentence on this page. StatPearls states: "Retrognathia or microgenia and unfavorable hyoid position are important to recognize preoperatively because they will both contribute to a poor surgical outcome, but addressing them is not a typical part of neck rejuvenation procedures."
Read that twice if you are about to spend money on this area. It says two things. These positions affect the result. And they are not what standard neck work changes. That is why recognising them beforehand is the difference between a realistic plan and a disappointing one.
Why does age change which of these is dominant?
Because the components change at different rates. The same person can have a fat problem at thirty and a muscle and skin problem at sixty, with the profile looking superficially similar throughout.
The rough progression:
- Younger necks are more often a fat question, with skin that still retracts well.
- From the forties onwards, skin elasticity declines and the fat that is present sits less tidily.
- By the mid fifties, platysmal banding commonly becomes visible, per the StatPearls timeline above.
- Throughout, jaw and hyoid position do not change at all. They were always there, and they become more obvious as the components in front of them alter.
The practical consequence: an assessment done ten years ago does not describe your neck now, and a conclusion you reached about yourself at twenty-five may simply be out of date.
Why do chin exercises not work on any of them?
Because none of the six categories is a weak muscle, and exercise only trains muscle.
Taking them in turn: fat is not removed by contracting the muscle underneath it, because muscles do not draw fuel preferentially from the fat sitting above them. Skin does not regain elasticity by being moved. Jaw and hyoid position are skeletal.
The platysma case is the interesting one, and it is worse than merely useless. The bands are caused by separation of the muscle's midline fibres, not by weakness. And StatPearls states that contracting the platysma accentuates the bands. So a routine built around repeatedly contracting that muscle is training in the wrong direction.
Chewing gum has the same problem in a different muscle group. The masseter is a chewing muscle at the angle of the jaw, and working it does nothing to the tissue under the chin.
What should you ask so you are not treated for the wrong thing?
Ask which of the six categories is dominant in your case, and ask what the plan does about the ones it cannot change. A good answer names a category and a limitation.
Questions that produce a useful consultation:
- "Which of these is the main problem in my neck: fat, skin, muscle, or where my jaw and hyoid sit?"
- "If it is fat, is it above the muscle or beneath it?"
- "How is my skin elasticity, and does that change what is realistic?"
- "Do I have platysmal bands, and are they visible at rest or only on movement?"
- "Is my chin position or hyoid position contributing, and what does that mean for the result?"
- "What will this plan not change?"
The last question is the one that separates an assessment from a sale. Every plan has something it does not address, and a clinician who names it without being pushed has told you something reliable about the rest of the conversation.
How is a neck profile assessed at Elegance Face Makeover, Surat?
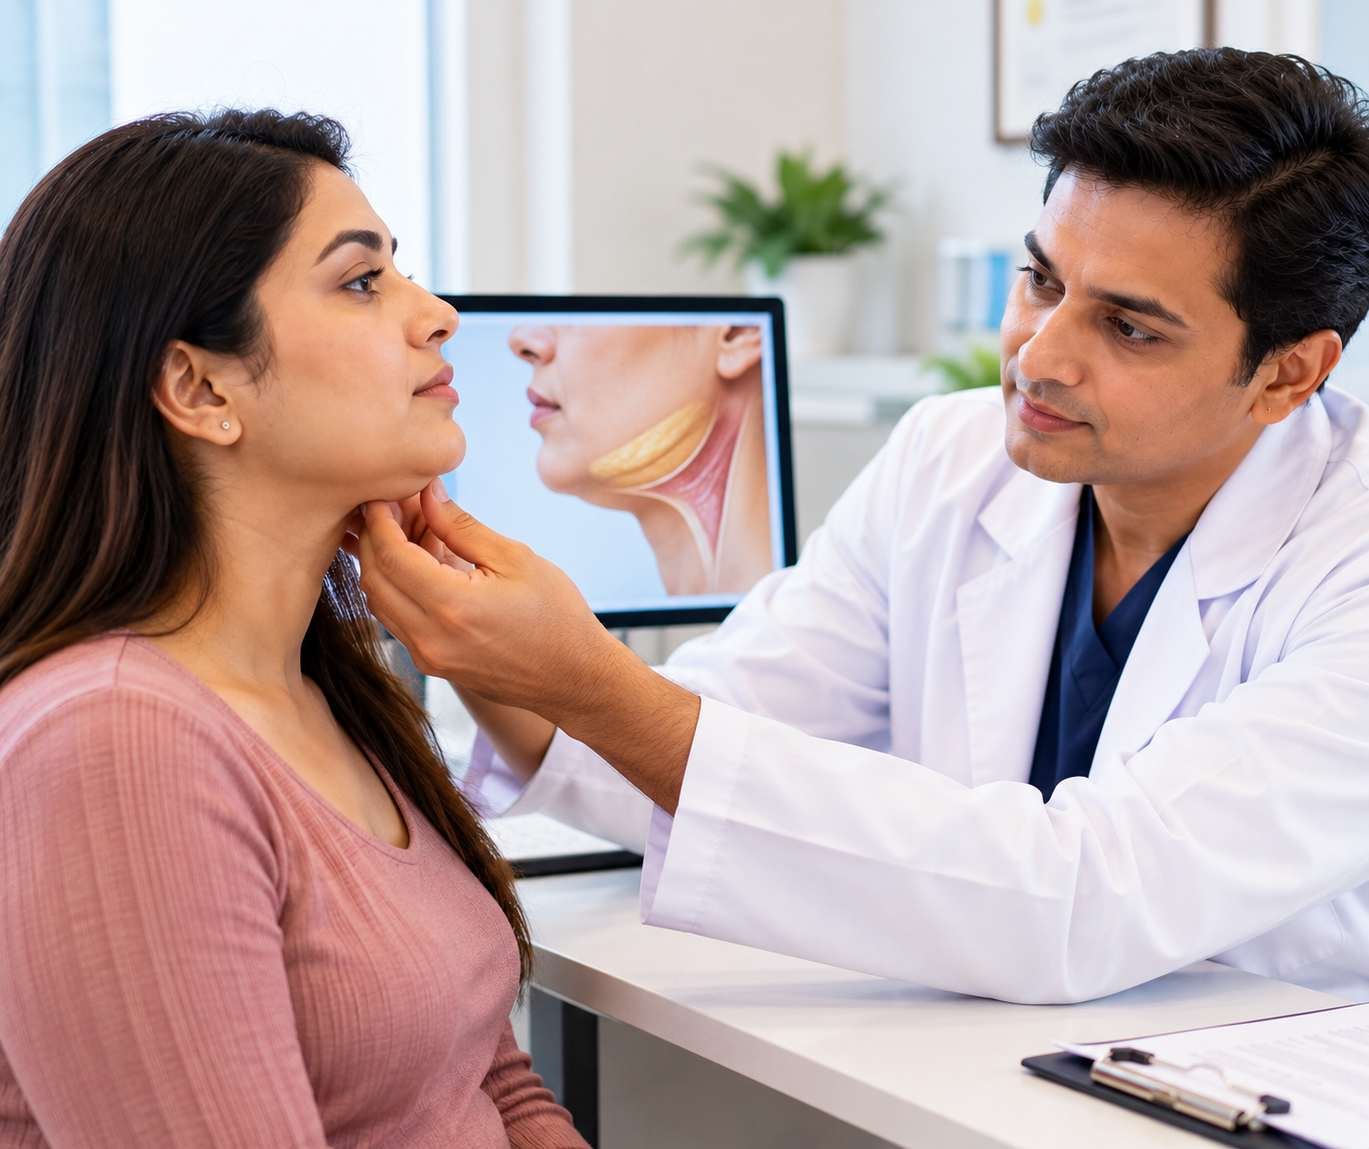
By working through the same categories in the same order: skin quality, then the fat layers, then the muscle, then the skeletal framework underneath. The assessment produces a category before anything else is discussed.
In our practice in Surat, the most common reason someone leaves a consultation with a different understanding than they arrived with is the profile photograph. People come convinced the problem is fat, having dieted hard and repeatedly, and the side view shows a chin position and a neck angle that were never going to respond to weight loss. That is a two minute finding, and it reframes the entire conversation.
The examination covers skin recoil, what can be gathered and in which layer, whether bands appear at rest or only on contraction, jaw and chin position in profile, and the angle between chin and neck. Once a category is established, options are a separate conversation, set out on our page on double chin reduction and in more detail in our post on what each double chin treatment actually does.
Next step
If you have already lost the weight and the profile has not followed, the useful next step is an assessment that names which category you are in, because that decides whether anything else is worth doing. Book through the Elegance contact page in Surat, and bring a side-on photograph with you.
This article is for education and is not a substitute for examination. Which component is dominant in your neck cannot be determined from a description or a photograph alone. Please consult Dr. Ashutosh A Shah or another qualified plastic or cosmetic surgeon about your own circumstances.